What are Thyroid Disorders?
A family of conditions where the body's metabolic master dial is set too low — or too high.
The thyroid is a 25-gram, butterfly-shaped gland at the base of your neck that sets the metabolic speed of every cell in your body — heart rate, temperature, energy production, weight regulation, even how fast you think. Thyroid disorders occur when this dial drifts in either direction: hypothyroidism (too little hormone — the engine idles: fatigue, weight gain, cold intolerance) or hyperthyroidism (too much — the engine races: weight loss, palpitations, anxiety). Thyroid disease affects roughly 12% of Americans in their lifetime, is 5–8 times more common in women, and in iodine-sufficient countries the leading cause is autoimmune: Hashimoto's disease for underactive, Graves' disease for overactive. The modern message: thyroid disorders are precisely diagnosable with a blood test and highly treatable — but they are lifetime conditions managed with a physician, never a shelf.
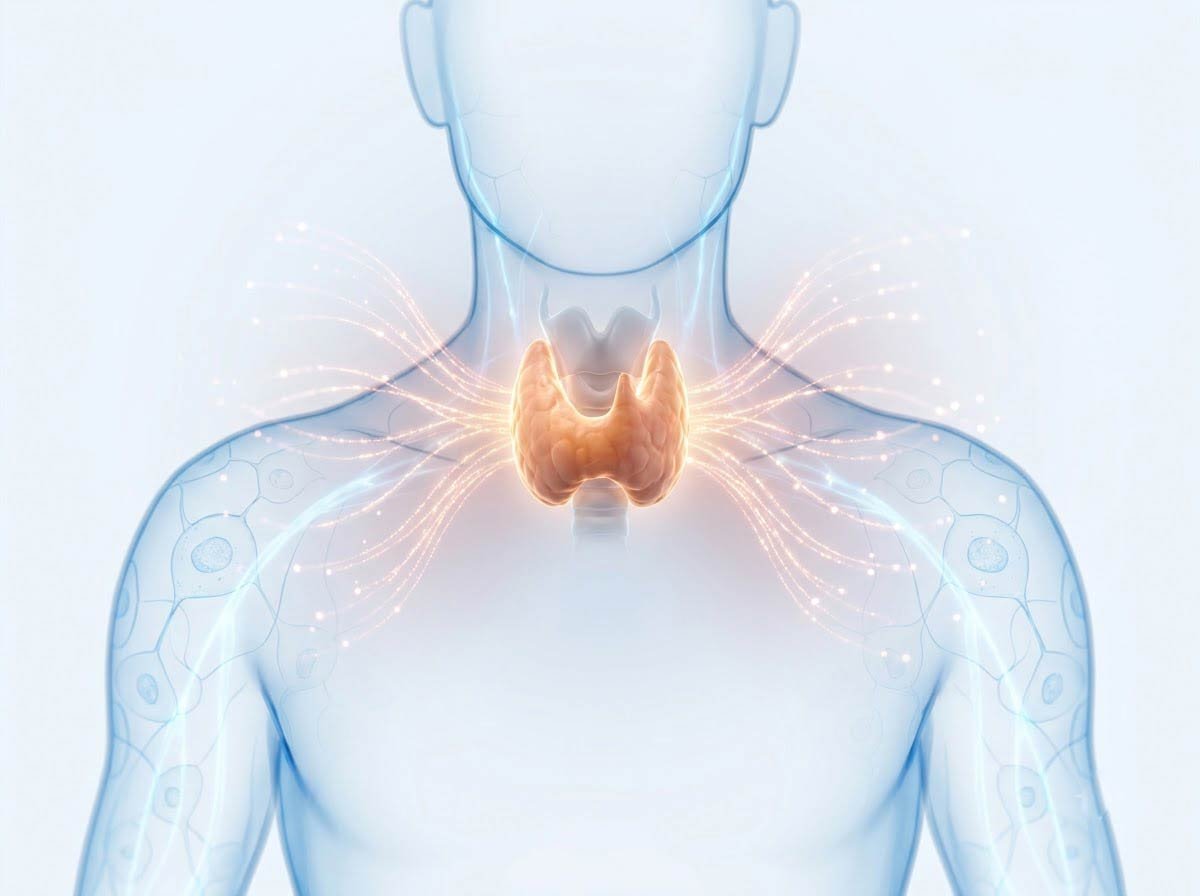
How Thyroid Disorders Connect
Understanding the Thermostat Loop
The thyroid runs on one of the body's elegant feedback loops — a thermostat. The hypothalamus releases TRH, the pituitary answers with TSH (thyroid-stimulating hormone), and the thyroid produces its hormones: mostly T4, the long-lived storage form, and a little T3, the active form. When circulating hormone runs low, the pituitary turns TSH UP to push the gland harder; when hormone runs high, TSH falls to near zero. This is why a single TSH reading is the master diagnostic — it reports what the pituitary thinks of the thyroid, from the one seat in the house with the best view.
Two refinements matter. First, about 80% of active T3 is made outside the thyroid — in the liver, muscle, and brain — by conversion enzymes (deiodinases) built around selenium: the gland produces the draft, the body edits it. Second, the system fails in two directions with two different personalities. Hypothyroidism is a slow, cold, quiet fade; hyperthyroidism is a racing, trembling, heat-producing alarm. Same gland, opposite failures — and the treatments are opposites too: replace what's missing, or suppress what's excessive.
- Hypothyroidism (underactive): the engine idles — fatigue, weight gain, cold intolerance, constipation, dry skin, hair thinning, slow heart rate, brain fog. The most common thyroid disorder.
- Hashimoto's thyroiditis: autoimmune destruction of the gland — the leading cause of hypothyroidism in iodine-sufficient countries, marked by TPO antibodies.
- Hyperthyroidism (overactive): the engine races — weight loss despite appetite, heat intolerance, palpitations, anxiety, tremor, loose stools, insomnia.
- Graves' disease: autoimmune stimulation of the gland — the leading cause of hyperthyroidism; can include bulging eyes (orbitopathy).
- Subclinical thyroid disease: TSH drifts outside range while hormone levels still read normal — the gray zone where treatment decisions are most individual.
- Goiter and nodules: structural enlargement or lumps — common, usually benign, evaluated by ultrasound and biopsy where indicated.
The Akron Schoolgirls: Iodized Salt's Origin Story
In 1917, surgeon David Marine began one of medicine's first large preventive trials: roughly 2,190 schoolgirls in Akron, Ohio, given small iodine doses through the school year, versus untreated controls. Akron sat in the old 'goiter belt' — the Great Lakes region where iodine-poor soil left populations deficient, and thyroid enlargement (goiter) was so common it was considered normal.
The result was decisive: iodine dramatically reduced goiter development. By 1924, iodized salt reached American tables — and over the following decades, the goiter belt vanished. It is one of the great public-health wins, and it carries this page's enduring paradox: the nutrient that prevents thyroid disease in deficiency causes it in excess. The window is real, and it has two edges.
Every adult with persistent fatigue, unexplained weight change, cold or heat intolerance, or menstrual changes should know their TSH. Typical reference range runs roughly 0.4–4.0 mIU/L — with pituitary reading high (TSH up) in underactive disease and near-zero in overactive. Diagnosis and every dose decision belong with a physician. Women planning pregnancy should know their TSH before conceiving — pregnancy tightens targets because maternal thyroid hormone builds the fetal brain. And one cross-connection worth remembering: unexplained high LDL cholesterol warrants a TSH check — low thyroid quietly raises cholesterol.
Your thyroid produces mostly T4 — a storage form. Roughly 80% of the active hormone your cells actually use is converted from T4 elsewhere, by enzymes built around selenium, in your liver and muscles. The gland writes the draft; the body edits it.
- Thyroid disease affects 5–8 times more women than men — screening symptoms in women deserves a lower threshold.
- Hashimoto's is the most common cause of hypothyroidism in iodized-salt countries; worldwide, iodine deficiency still leads.
- Hypothyroidism quietly raises LDL cholesterol — unexplained high cholesterol deserves a TSH check.
- Levothyroxine absorption is blocked by iron, calcium, and coffee — timing the morning dose is part of the treatment.